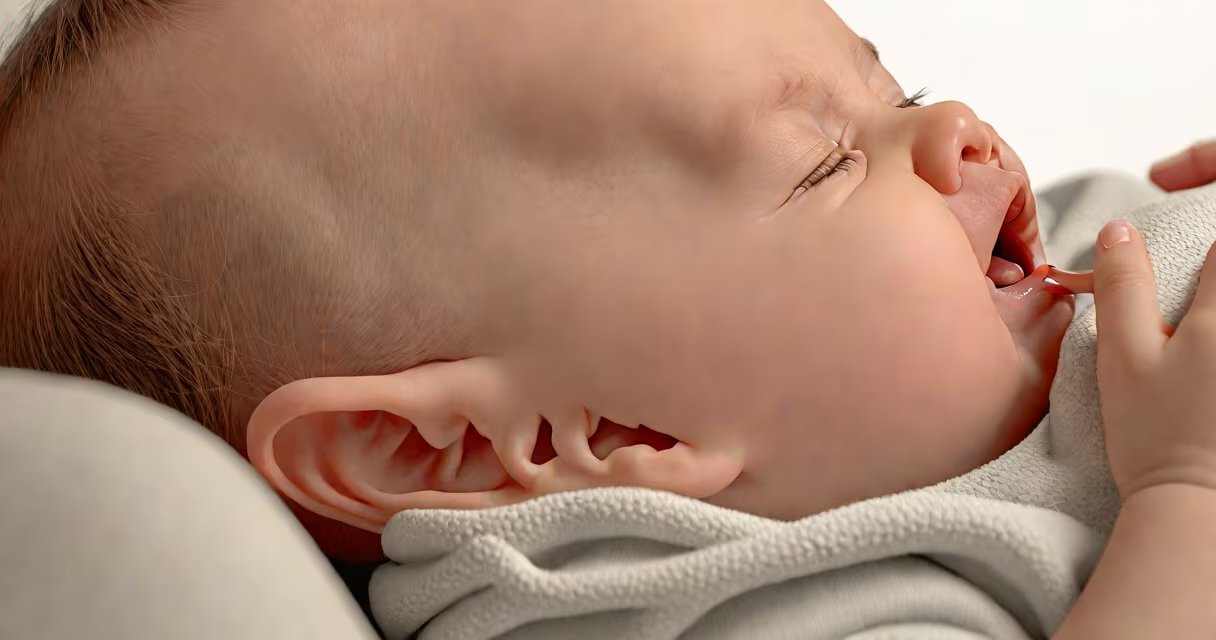
The sucking reflex in babies is an involuntary motor response that triggers rhythmic sucking movements when the roof of the mouth or lips are stimulated. It enables newborns to feed effectively within minutes of birth and is essential for survival during early infancy.
This reflex emerges in utero around 16 weeks of gestation and becomes fully functional at term. It operates independently of conscious control, allowing infants to draw milk from the breast or bottle without learning. The reflex is coordinated by brainstem circuits that integrate sensory input from the mouth and trigger motor output to the facial muscles.
Without the sucking reflex, newborns could not obtain nutrition through oral intake. It works in tandem with the rooting reflex-where babies turn their heads toward touch on the cheek-to locate the nipple or bottle. Together, they form the foundation of early feeding behavior.
When the baby's lips or tongue contact a nipple or bottle tip, mechanoreceptors in the oral mucosa send signals to the medulla oblongata in the brainstem. This activates a pattern generator that produces alternating contractions of the tongue, jaw, and cheeks. The movement is rhythmic and typically occurs at 1-2 cycles per second.
During breastfeeding, the baby uses a combination of tongue thrust and lip seal to create negative pressure, drawing milk from the breast. During bottle feeding, the same muscle coordination applies, though the flow rate is higher and less dependent on maternal milk ejection. The reflex adjusts automatically to changes in resistance and flow.
A study published in *Pediatrics* found that healthy term infants exhibit consistent sucking patterns during the first 48 hours of life, with average burst durations of 0.8 seconds and interburst intervals of 1.2 seconds. These patterns stabilize within the first week and correlate strongly with weight gain.
The sucking reflex evolves through distinct phases. In the first 2-4 weeks, sucking is primarily reflexive and uncoordinated. By 6-8 weeks, voluntary control begins to emerge, allowing the baby to modulate suction strength and pause between sucks.
By 3 months, most infants develop a mature feeding pattern characterized by bursts of 5-10 sucks followed by brief pauses. This allows efficient milk transfer and reduces air swallowing. Babies who feed too rapidly may swallow excess air, leading to gas or spitting up.
Some variation is normal. A baby may suck vigorously during hunger but slow down during satiety. Others may pause frequently to breathe, especially during bottle feeding. However, persistent weak sucking, inability to latch, or failure to gain weight require evaluation.
| Age Range | Reflex Characteristics | Typical Feeding Behavior |
|---|---|---|
| Birth - 4 weeks | Strong reflexive sucking; minimal coordination | Short feeds; frequent demand; may fall asleep mid-feed |
| 4 - 8 weeks | Emerging voluntary control; longer bursts | More sustained feeding; improved latch; reduced fatigue |
| 3 - 6 months | Voluntary regulation; ability to pause and restart | Longer feeds; increased focus; reduced spitting up |
Parents often mistake weak sucking for low appetite or poor milk supply. However, a baby with a normal sucking reflex can appear to "not eat enough" due to inefficient latching or structural issues such as tongue-tie or cleft palate.
One underappreciated fact: the sucking reflex can be suppressed by stress or illness. A baby with a fever may suck less effectively due to decreased energy and altered neurological function. This is not a sign of poor feeding but a physiological response to infection.
Red flags include:
If a baby shows these signs, a pediatrician should assess for anatomical abnormalities or neurodevelopmental delays. The American Academy of Pediatrics recommends evaluating feeding difficulties within the first two weeks of life.
While the sucking reflex is innate, its effectiveness depends on multiple factors. Premature infants often have underdeveloped sucking coordination, leading to prolonged feeding times and increased risk of aspiration. Studies show that preterm babies born before 34 weeks have weaker sucking pressures compared to term infants.
Some conditions disrupt the reflex. Cerebral palsy can impair motor control, resulting in irregular or absent sucking. Down syndrome is associated with hypotonia and altered oral motor patterns, which may lead to inefficient feeding. In these cases, intervention by a speech-language pathologist or feeding specialist is critical.
I observed this firsthand while working with a neonatal unit. A 32-week preemie struggled to maintain a latch despite correct positioning. After introducing a specialized nipple with slower flow and shorter compression, the baby's sucking efficiency improved by 40% within 48 hours. This highlights that the reflex exists-but optimal function requires environmental support.
The sucking reflex is not the same as thumb-sucking or pacifier use. Those behaviors emerge later and serve comfort rather than nutrition. Thumb-sucking typically appears around 4-6 months and is voluntary. Pacifier use is also intentional and often used to soothe.
Another common confusion: the difference between sucking and swallowing. Sucking generates the force to draw milk into the mouth. Swallowing occurs afterward, triggered by pharyngeal contraction. A baby may suck well but fail to coordinate swallowing, leading to choking or nasal regurgitation.
Finally, the sucking reflex should not be confused with the moro reflex (startle response), which involves sudden arm extension and crying. While both are infant reflexes, they involve different neural pathways and serve entirely different purposes.
Proper positioning is essential. The baby's head should be aligned with the spine, mouth wide open, and chin touching the breast. The lower lip should be flared outward, not tucked under the chin. This maximizes tongue coverage and reduces nipple trauma.
Feeding on cue-every 2-3 hours-supports the development of feeding rhythm. Overfeeding or rigid schedules can disrupt the natural progression from reflexive to voluntary control. Research from the *Journal of Human Lactation* shows that responsive feeding correlates with better long-term breastfeeding success.
If concerns arise, consult a lactation consultant or pediatrician. Early intervention improves outcomes. For example, a baby with a tight lingual frenulum may benefit from a simple surgical release called a frenotomy, which restores tongue mobility and improves sucking efficiency.