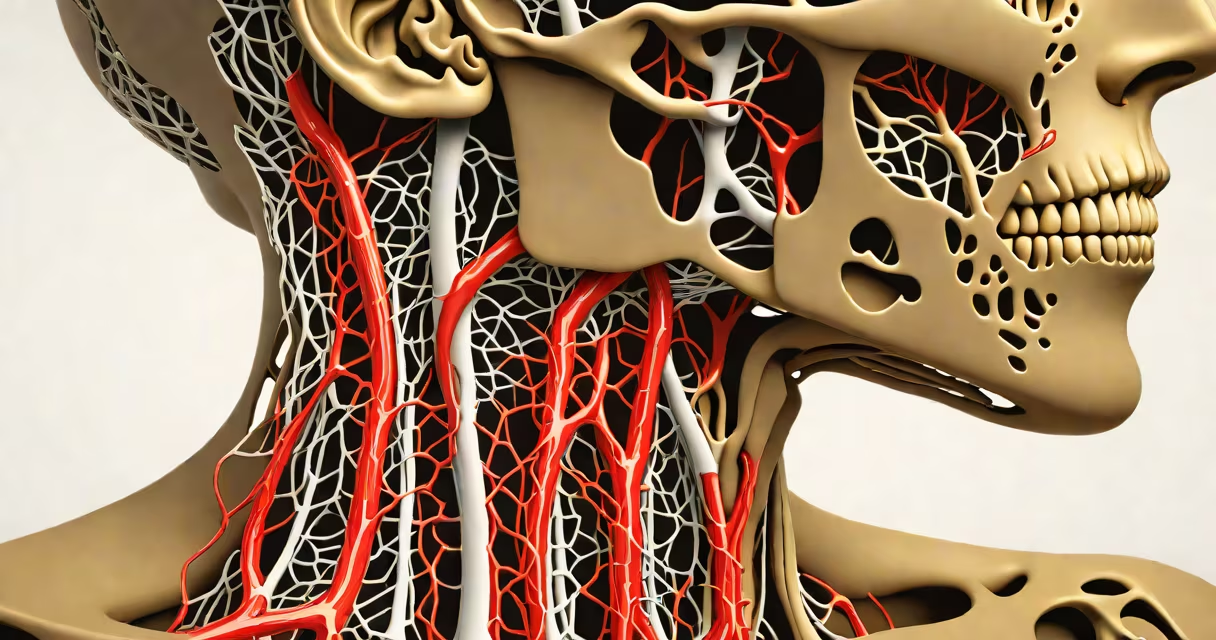
Neck anatomy vessels refer to the network of arteries and veins in the neck responsible for delivering oxygenated blood to the brain and draining deoxygenated blood from the head and face. These structures include the internal and external carotid arteries, the internal and external jugular veins, and the vertebral arteries.
The neck houses critical vascular pathways that support cerebral perfusion and venous return. Damage to any of these vessels can lead to stroke, hemorrhage, or impaired neurological function. The primary arterial supply to the brain originates from the internal carotid arteries, which enter the skull through the carotid canal. The vertebral arteries, arising from the subclavian arteries, ascend through the transverse foramina of the cervical vertebrae and join to form the basilar artery at the base of the brain.
Veins in the neck primarily drain blood from the brain, face, and neck tissues. The internal jugular vein runs alongside the internal carotid artery within the carotid sheath and empties into the subclavian vein. The external jugular vein drains superficial regions of the head and neck and empties into the subclavian vein at the base of the neck. Both systems are essential for maintaining intracranial pressure and preventing venous congestion.
Arteries in the neck deliver oxygen-rich blood to the brain via the internal carotid and vertebral arteries. The internal carotid enters the skull at the petrous portion of the temporal bone and divides into anterior and middle cerebral arteries. The vertebral arteries travel through the cervical spine's transverse foramina, then unite at the pontine level to form the basilar artery, which supplies the posterior brainstem and cerebellum.
Veins collect deoxygenated blood from the brain and face. The internal jugular vein begins at the jugular foramen and travels down the neck, receiving tributaries from the facial, retromandibular, and superior thyroid veins. It empties into the brachiocephalic vein at the root of the neck. The external jugular vein forms from the union of the posterior division of the retromandibular vein and the posterior auricular vein, draining the scalp and face.
These vessels operate under precise hemodynamic control. Blood flow to the brain remains stable despite changes in posture due to autoregulation mechanisms in cerebral arterioles. The carotid sinus, located at the bifurcation of the common carotid artery, monitors blood pressure and triggers reflex adjustments in heart rate and vascular resistance.
The neck contains several distinct vessel groups based on origin, function, and anatomical location:
| Vessel Type | Origin | Function | Key Anatomical Landmark |
|---|---|---|---|
| Internal carotid artery | Common carotid artery (at C4) | Supplies anterior and middle cerebral arteries | Carotid bifurcation at C4 level |
| External carotid artery | Common carotid artery (below bifurcation) | Supplies face, scalp, and neck muscles | Branches to facial, superficial temporal, and occipital arteries |
| Vertebral artery | Subclavian artery (originates at lateral aspect of first rib) | Supplies posterior brainstem and cerebellum | Enters transverse foramina of C6-C1 |
| Internal jugular vein | Jugular foramen (skull base) | Drains cerebral and facial blood | Runs with internal carotid in carotid sheath |
| External jugular vein | Union of retromandibular and posterior auricular veins | Drains superficial head and neck | Exits below the angle of the mandible |
Each vessel operates within a defined fascial compartment. The carotid sheath, formed by the deep cervical fascia, encloses the internal carotid artery, internal jugular vein, and vagus nerve. This structure protects important neurovascular bundles and prevents migration during neck movement.
A non-obvious fact: the vertebral arteries are not solely responsible for posterior circulation. They contribute to the posterior inferior cerebellar artery (PICA), which supplies the medulla and cerebellar tonsils. A single vertebral artery occlusion may not cause symptoms if collateral flow from the opposite side maintains perfusion-a phenomenon known as the "vertebrobasilar anastomosis."
Neck anatomy vessels are central to diagnostic imaging, surgical planning, and emergency care. Carotid ultrasound assesses plaque burden and stenosis in patients at risk for ischemic stroke. Doppler flow measurements help determine whether stenosis exceeds 70%, a threshold for considering carotid endarterectomy.
In trauma, penetrating injuries to the neck require rapid assessment of vascular integrity. A stab wound near the carotid triangle may damage the internal carotid artery, leading to catastrophic hemorrhage. The "neck trauma algorithm" includes CT angiography to detect vascular injury, especially in patients with signs of shock or expanding hematoma.
During surgical procedures such as thyroidectomy or parathyroidectomy, surgeons must identify and preserve the superior and inferior thyroid arteries and the external branch of the superior laryngeal nerve, which lies close to the superior thyroid artery. Misidentification can result in vocal cord paralysis or hypoparathyroidism.
I once performed a cadaver dissection where the internal jugular vein was accidentally punctured during exposure of the carotid sheath. The resulting hemorrhage required immediate compression and surgical repair. This experience reinforced how fragile these vessels are-even in controlled settings-and why anatomical precision matters.
Many confuse the external carotid artery with the facial artery. The facial artery arises from the external carotid and courses along the mandible, not the neck itself. It supplies the skin and muscles of the face but does not enter the cranial cavity.
Another misconception: the internal jugular vein is often thought to be a passive drainage vessel. In reality, it plays an active role in regulating intracranial pressure. During straining or coughing, increased intrathoracic pressure can impede venous outflow, causing transient increases in intracranial pressure-known as the Valsalva effect.
Some assume all neck vessels are visible externally. The internal carotid and vertebral arteries lie deep within the skull and cannot be palpated. Only superficial vessels like the external jugular vein and facial artery are accessible to physical exam.
The term "carotid artery" is often used generically. But the internal carotid artery is the primary supplier to the brain. The external carotid artery serves the face and scalp. Confusing them leads to incorrect clinical decisions-such as misdiagnosing a pulsatile neck mass as a carotid aneurysm when it's actually a dilated external carotid artery.