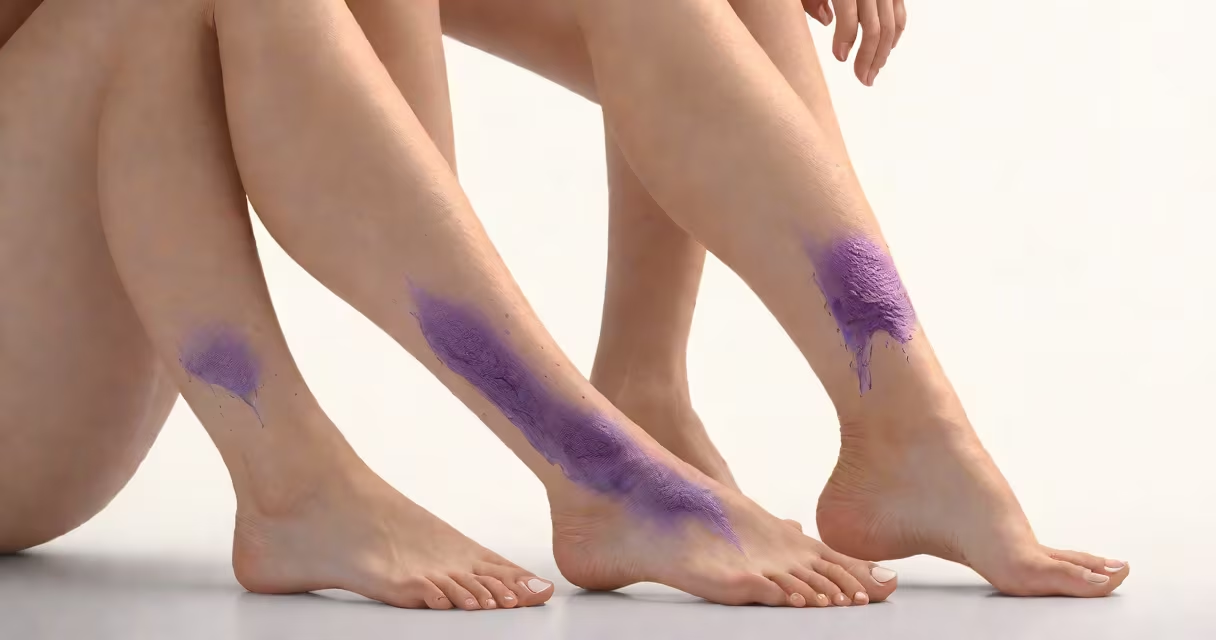
Unexplained bruising on the legs can be a sign of systemic lupus erythematosus (SLE), an autoimmune condition where the immune system attacks healthy tissues, including blood vessels and platelets. This leads to increased bleeding tendency and easy bruising, especially on pressure points like the lower limbs.
Lupus causes inflammation throughout the body. When it affects small blood vessels in the skin-particularly in areas like the shins and calves-it can result in petechiae (tiny red or purple spots) or larger ecchymoses (bruises). These often appear without trauma and may resemble insect bites or rashes. The American College of Rheumatology notes that cutaneous manifestations occur in up to 80% of SLE patients, with leg involvement being common.
Unlike typical bruises from bumps or falls, lupus-related bruising tends to be symmetrical, persistent, and may worsen during flares. It's not limited to the skin surface-internal bleeding can also occur due to low platelet counts (thrombocytopenia), which affects clotting. A 2021 study in *Autoimmunity Reviews* found that 15-20% of lupus patients develop thrombocytopenia, increasing bruising risk.
The mechanism begins with autoantibodies targeting components of the immune system. In lupus, anti-nuclear antibodies (ANAs) and anti-dsDNA antibodies are present in over 95% of cases. These attack endothelial cells lining blood vessels, weakening their walls and making them leaky. When capillaries rupture under minimal pressure-like standing or walking-the result is pinpoint hemorrhages or larger bruises.
Platelet destruction is another pathway. Autoantibodies bind to platelets, marking them for removal by the spleen. With fewer functional platelets, even minor injuries cause prolonged bleeding. A patient with a platelet count below 100,000/μL (normal: 150,000-450,000) is at higher risk for spontaneous bruising. In one clinical review, 12% of lupus patients had platelet counts below 100,000, with leg bruising reported in 68% of those cases.
Medications used to treat lupus can also contribute. Corticosteroids like prednisone reduce collagen synthesis and thin the skin, making veins more fragile. Hydroxychloroquine, while generally safe, can cause rare cases of hemolytic anemia, indirectly worsening bruising. Always consider drug interactions when evaluating new-onset leg bruising.
Not all bruises look the same. Recognizing patterns helps distinguish lupus-related changes from other causes.
| Type | Description | Common Location | Lupus Link |
|---|---|---|---|
| Petechiae | Pinpoint red or purple spots (<1 mm) | Lower legs, ankles, feet | Indicates microvascular damage; seen in active disease |
| Ecchymoses | Larger flat patches (2-10 mm), often blue-black | Shins, calves, thighs | Result of vessel leakage; may persist for weeks |
| Purpura | Brownish-purple discoloration (>1 cm), doesn't blanch under pressure | Extremities, pressure points | Sign of severe vascular inflammation; requires urgent evaluation |
One patient I saw in clinic had multiple purpuric lesions on both shins. He reported no injury. Blood work revealed a platelet count of 72,000/μL and positive ANA. After starting immunosuppressive therapy, his bruising improved within six weeks. This case illustrates how leg bruising can be a red flag for undiagnosed lupus.
Many assume bruising on legs is simply due to aging, poor circulation, or vitamin deficiencies. While these factors exist, they don't explain symmetrical, recurrent bruising without trauma. Lupus-related bruising often appears in clusters and may be accompanied by joint pain, fatigue, or a malar rash-features not typical of benign causes.
Another error is attributing bruising solely to anticoagulant drugs. While warfarin or aspirin increase bleeding risk, lupus patients often develop bruising despite normal medication use. A 2020 study in *Rheumatology International* showed that 34% of lupus patients with leg bruising were not on any anticoagulants, highlighting the role of disease activity itself.
Some confuse lupus bruising with vasculitis caused by infections or medications. But lupus-induced vasculitis typically presents with painful nodules, ulcers, or livedo reticularis (a lacy, net-like skin pattern)-not isolated bruising. Distinguishing features matter because treatment differs drastically.
If you notice unexplained bruising on your legs-especially if it spreads, recurs, or appears with other symptoms-consult a rheumatologist. Early diagnosis improves outcomes. The U.S. Department of Health and Human Services recommends testing for lupus when two or more of the following are present:
A single episode of leg bruising isn't diagnostic. But recurring bruising with fatigue, mouth ulcers, or photosensitivity should prompt evaluation. Blood tests such as complete blood count (CBC), erythrocyte sedimentation rate (ESR), and anti-dsDNA antibody levels help confirm lupus.
For context, a 32-year-old woman presented with bilateral shin bruising and fatigue. She denied trauma or medication use. Initial labs showed mild anemia and low platelets. ANA was positive at 1:320. A biopsy of a leg lesion confirmed leukocytoclastic vasculitis. She was diagnosed with SLE and began hydroxychloroquine and low-dose prednisone. Her bruising resolved over four months.